

Epitalon reliably upregulates telomerase and extends telomeres in cultured normal human cells, and it triggers a distinct ALT-based extension pathway in certain cancer lines. No placebo-controlled human trial has confirmed an anti-aging or lifespan benefit in people, and the compound is not FDA-approved. What exists is a mechanistically consistent in vitro and animal data set sitting on top of a thin, decades-old, largely unreplicated human literature.
TL;DR:
- Epitalon has shown dose-dependent telomere extension and increased telomerase activity in normal human cells, but effects in cancers vary depending on the mechanism, with ALT activation being faster.
- Most animal lifespan and tumor reduction data come from a single research group and lack independent replication, making its longevity effects uncertain and unconfirmed at broader research levels.
- No modern, placebo-controlled human trial has demonstrated that Epitalon slows aging or extends lifespan, and the existing human data is mostly on epithalamin, not the synthetic peptide.
- Safety data is limited and unmonitored, with concerns about potential cancer risks stemming from telomerase reactivation, requiring thorough, long-term safety studies before human use.
- Critical next steps include detailed pharmacokinetic, dosing, and mechanistic studies, independent replication, and well-designed clinical trials before Epitalon can be considered a proven anti-aging intervention.
Table of Contents
- What Does Epitalon Research Actually Tell Us So Far?
- What Do the In Vitro Numbers Actually Show?
- Do Animal Studies Support Longer Lifespan or Healthspan?
- What Does Human Data Actually Show, and Where Are the Gaps?
- What Are the Known and Unknown Safety Risks?
- What Studies Would Actually Move This Field Forward?
- Data Peptides’ View on Where the Evidence Actually Stands
- Sourcing Research-Grade Epitalon for Laboratory Work
- Key Papers and Regulatory Documents for Deeper Reading
- Sources
- FAQ
What Does Epitalon Research Actually Tell Us So Far?
Epitalon is the synthetic tetrapeptide Ala-Glu-Asp-Gly, abbreviated AEDG. It was designed as a stable analog of epithalamin, the bovine pineal gland extract that Vladimir Khavinson’s laboratory in St. Petersburg studied for decades. Epithalamin is a mixture of peptides pulled from animal tissue; Epitalon is one isolated, synthesized fragment believed to carry the extract’s most relevant activity. That distinction matters more than most summaries admit, because a large share of the “Epitalon” literature you’ll find cited online actually tested epithalamin in Russian clinical cohorts, not the synthetic four-amino-acid compound sold today.
The mechanistic case for Epitalon rests on a handful of interlocking claims about telomere biology. Telomeres are the repetitive DNA caps at the ends of chromosomes that shorten with each cell division; telomerase, an enzyme built around the catalytic subunit hTERT, can rebuild that cap and slow or reverse the shortening. Researchers have proposed that Epitalon acts on this system in a few distinct ways:
- Upregulating hTERT gene expression, which increases telomerase enzymatic activity in cells that already carry the machinery for it.
- Modulating epigenetic markers tied to circadian and pineal gland signaling, since epithalamin’s original research context was melatonin regulation, not telomere biology directly.
- Triggering the alternative lengthening of telomeres (ALT) pathway, a telomerase-independent mechanism normally seen in a minority of cancers, in specific malignant cell lines.
A 2025 study gives the clearest modern look at this. It reported dose-dependent telomere extension in normal human epithelial and fibroblast cells, driven by measurable increases in hTERT mRNA and telomerase enzymatic activity. In two breast cancer cell lines, the same peptide extended telomeres through a completely different route: ALT activation rather than telomerase upregulation. That’s a meaningful split. It means the compound doesn’t do one thing to telomeres; it does different things depending on which molecular toolkit the cell already has running.
Data point: In BT474 breast cancer cells, telomere length reached roughly 8 kb at a dose of 0.2 μg/ml, and higher doses produced a lower rate of extension than that 0.2 μg/ml point, a nonlinear dose response that complicates any simple “more is better” assumption researchers might carry into their own protocols.
Confirming any of this requires specific lab techniques, and each comes with its own blind spots; sourcing validated primary antibodies and research reagents is essential for reliable orthogonal telomere or ALT assays. The telomeric repeat amplification protocol (TRAP) measures telomerase enzymatic activity but can be sensitive to sample handling and PCR artifacts. Quantitative PCR (qPCR) estimates average telomere length across a cell population but can’t tell you which individual cells changed. The c-circle assay detects a specific DNA structure associated with ALT activity, and PML immunofluorescence (PML IF) looks for the nuclear bodies that cluster around ALT-associated telomeres. None of these methods, used alone, proves a mechanism beyond reasonable doubt. Researchers who see a clean TRAP signal but skip c-circle or PML confirmation in a cancer-adjacent line risk overstating what they’ve actually shown.
What Do the In Vitro Numbers Actually Show?
The strongest quantitative signal in the current literature comes from that same 2025 replication study, and the details matter more than the headline. Normal human epithelial cells and fibroblasts showed telomere lengthening that scaled with dose, up to a point, and tracked with rising hTERT transcript levels and telomerase enzymatic activity over the incubation period. That’s a coherent, biologically plausible pattern: a peptide nudges gene expression, the enzyme ramps up, the telomere responds over time.
The cancer cell response looked different in both mechanism and timing. Breast cancer lines reached measurable telomere extension faster, but the driving pathway was ALT rather than telomerase, and the dose response was nonmonotonic rather than a straight line, and the 0.2 μg/ml concentration outperformed higher doses tested in the same experiment. Any researcher designing a follow-up study needs to treat “cancer cell” and “normal cell” responses as two separate biological questions, not two data points on the same curve.
A few things stand out for anyone trying to reproduce or extend this work:
- Timing asymmetry. Normal cells needed longer incubation windows to show telomerase-driven extension, while ALT-mediated extension in cancer lines showed up faster, which suggests the two mechanisms operate on different biological clocks.
- Dose nonlinearity. The peak effect in BT474 cells sat at a low concentration, not the highest dose tested, which argues against assuming a simple dose-response relationship in any new protocol.
- Assay sensitivity. PCR-based telomerase and telomere-length assays can overestimate activity, particularly in mixed or heterogeneous cell populations, which is why orthogonal confirmation matters.
- Cell line heterogeneity. Two breast cancer lines don’t represent all telomerase-negative or ALT-prone cancers, so generalizing to other tumor types from this data alone is premature.
The overestimation risk with PCR and TRAP-based methods deserves its own callout, because it shapes how much confidence to place in any single-assay result. Southern blot terminal restriction fragment analysis and telomere fluorescence in situ hybridization (telomere FISH) offer independent, non-PCR confirmation of telomere length changes, and pairing c-circle assay results with PML IF gives a second line of evidence for ALT specifically. A result that holds up across two assay families is far more trustworthy than one that only shows up under TRAP or qPCR.
Pro Tip: If you’re planning a replication attempt, run your normal-cell and cancer-cell arms as fully separate experiments with matched vehicle controls for each, not a shared control group. The mechanisms diverge enough that pooling controls can mask real effects in either direction.
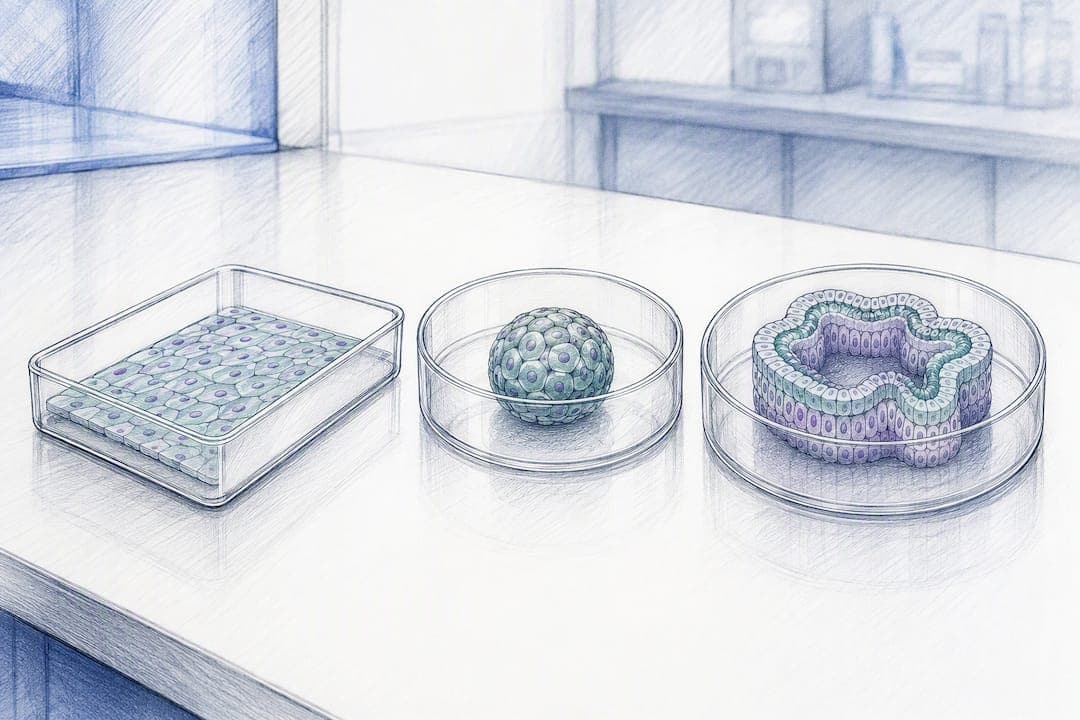
Practical experimental design also matters beyond the assay choice itself. Standard 2D monolayer culture is the format used in the existing published work, which means anyone moving to 3D spheroid or organoid models is extending the evidence base rather than confirming it. Culture conditions, including serum concentration and passage number, can shift baseline telomerase activity independent of any treatment, so documenting and controlling for those variables is not optional if you want a result anyone else can trust.
Do Animal Studies Support Longer Lifespan or Healthspan?
Animal data on Epitalon and its parent extract epithalamin report lifespan extension and reduced tumor incidence in several rodent studies, but almost all of this evidence traces back to one research network, and independent labs have not broadly replicated it. Khavinson and longtime collaborator Vladimir Anisimov published a substantial body of work across multiple decades showing increased median lifespan in specific mouse strains treated with epithalamin, alongside reports of Drosophila lifespan extension and reduced spontaneous tumor rates in some treated cohorts.
That’s a genuinely interesting data set, and it’s also a genuinely narrow one. The core findings on lifespan and tumor incidence come overwhelmingly from a single, tightly connected group of investigators, a pattern that a comprehensive review of the compound flagged directly: the evidence is concentrated in the Khavinson and Anisimov research network, with most reports lacking independent, modern replication outside that circle. Major independent longevity research programs, the kind that run large multi-lab aging interventions testing panels of compounds side by side, have not, to date, put Epitalon through that kind of scrutiny.
A few specific patterns from the animal literature are worth flagging for anyone weighing this evidence:
- Reported lifespan gains varied by mouse strain and study design, with no single, consistent effect size across the body of work.
- Reduced tumor incidence appeared in some treated cohorts, but tumor biology in short-lived rodent strains doesn’t map cleanly onto human cancer risk.
- Drosophila lifespan studies add a second species to the picture but come from the same limited set of research groups.
- No large, blinded, multi-site animal trial with pre-registered endpoints has tested Epitalon against the standard aging-intervention comparators used in modern longevity science, things like rapamycin or caloric restriction protocols.
Why does replication concentration matter this much? Because single-lab effects, even honest and carefully run ones, are vulnerable to lab-specific husbandry conditions, strain substructure, diet composition, and dozens of other variables that never show up in a methods section but can drive an effect that doesn’t travel. Nothing here suggests fraud or error. It suggests exactly what a thin evidence base looks like: promising, internally consistent, and unconfirmed by anyone outside the group that generated it.
What Does Human Data Actually Show, and Where Are the Gaps?
No completed, placebo-controlled clinical trial has tested synthetic Epitalon in humans and shown it slows aging, extends lifespan, or improves a validated clinical endpoint. Nearly everything cited as “human Epitalon research” is actually human data on epithalamin, the original bovine pineal extract, gathered decades ago under trial designs that don’t meet the reporting or blinding standards expected today.
That distinction is the single most important thing a researcher can carry out of this section. Epithalamin trials and synthetic Epitalon trials are not the same evidence base, even though the two names get used almost interchangeably in supplement marketing and forum discussion. One historical epithalamin trial treated 266 elderly adults over a two to three-year period and reported improved functional indices on long-term follow-up, a result frequently cited as supporting evidence for anti-aging effects. But as a comprehensive evidence summary on the compound notes, most of the original reports were published outside modern peer-reviewed channels, many not translated into English, and none used the placebo controls or blinding protocols that would let a modern reviewer rule out expectation effects or regression to the mean in an elderly cohort followed for years.
Statistic to hold onto: that 266-person, multi-year epithalamin cohort is one of the largest human data points in the entire literature, and it still falls short of a controlled trial design. Size alone didn’t buy rigor.
What’s genuinely missing before anyone can call Epitalon’s human effects established:
- A registered, placebo-controlled randomized trial with a pre-specified primary endpoint, run under modern Good Clinical Practice standards.
- Basic human pharmacokinetic data: absorption, half-life, tissue distribution, and clearance, none of which appear to be published for the synthetic peptide.
- A dose-ranging phase 1 safety study establishing tolerability before any efficacy claim is tested.
- Independent replication of any positive finding by a lab with no historical connection to the original research group.
- Long-term follow-up, ideally years, given that telomere and aging-related endpoints move slowly and can be confounded by short observation windows.
Until those pieces exist, “Epitalon and aging” claims aimed at humans remain a hypothesis extrapolated from cell culture and animal data, dressed in decades-old epithalamin observations that don’t transfer cleanly to the synthetic peptide sold as a research chemical today. A related but chemically distinct peptide history, including work on thymic peptides like Thymosin Alpha-1, shows a similar pattern: promising mechanistic and animal data taking far longer to clear the human trial bar than early enthusiasm suggested.
What Are the Known and Unknown Safety Risks?
The honest safety answer is that the known adverse event profile from historical trials is limited, and the unknowns are larger than the knowns. Reported adverse events in older epithalamin trials were generally mild, but “generally mild” is doing a lot of work in a data set built on unblinded, poorly monitored studies conducted before modern adverse-event reporting standards existed. Nobody has run the kind of rigorous, monitored phase 1 safety trial that would catch rare or delayed effects in a systematic way.
The theoretical cancer risk deserves direct treatment rather than vague hand-waving, because it flows straight from the mechanism. Telomerase reactivation is one of the hallmarks cancer biologists watch for, since unlimited replicative capacity is a defining feature of malignant cells. A peptide that upregulates telomerase in normal cells and separately activates the ALT pathway in certain cancer lines is not automatically dangerous, but it raises a legitimate question that only controlled, longer-duration studies can answer: does chronic exposure shift the risk profile of cells that are already on the edge of dysregulated growth? Nobody has that answer yet, in either direction.
Regulatory movement in 2026 sharpened this picture without resolving it. On July 24, 2026, the FDA’s Pharmacy Compounding Advisory Committee voted to recommend Epitalon-related bulk substances for potential inclusion on the 503A list, a pathway that governs compounding pharmacies. That vote is nonbinding, and no formal approval or listing decision has been issued. Epitalon remains unapproved as a drug in the United States. FDA staff reviewers flagged incomplete substance characterization, inadequate human safety data, and unresolved long-term risks including immunogenicity and aggregation potential, concerns that echo the exact gaps this article keeps circling back to.
For institutional review boards and investigators weighing a research proposal involving Epitalon in humans, a few practical points follow directly from this record:
- Treat pharmacokinetic and dose-tolerability data as prerequisites, not afterthoughts, given that essentially none exists in peer-reviewed form.
- Build in longer safety monitoring windows than a typical short peptide study, given the telomerase mechanism’s theoretical link to cell proliferation risk.
- Require sourcing documentation, including certificates of analysis, for any material used in animal or in vitro work, since substance characterization gaps were an explicit FDA staff concern.
- Keep any current work strictly within laboratory research use; this is not an approved therapeutic and shouldn’t be positioned as one in any protocol or consent language.
What Studies Would Actually Move This Field Forward?
Closing the gap between “interesting mechanism” and “usable clinical answer” requires a specific, ordered sequence of studies, not just more of the same cell culture work repeated in new labs.
- Pharmacokinetic characterization first. Establish absorption, distribution, half-life, and clearance in an animal model before any human dosing conversation starts.
- Dose-ranging phase 1 safety trials. Small, closely monitored human cohorts focused purely on tolerability and adverse events, not efficacy.
- Orthogonal mechanistic confirmation. Pair TRAP or qPCR telomere data with Southern blot or telomere FISH, and confirm any ALT signal with both c-circle assay and PML IF, before publishing mechanism claims.
- Independently replicated animal lifespan studies. Multi-site, pre-registered protocols run by labs with no prior connection to the original research network, using standardized strains and blinded outcome assessment.
- Randomized, placebo-controlled human efficacy trials. Only after the first four steps are complete, with pre-specified primary endpoints and adequate sample size calculated in advance.
Pro Tip: Pre-registration matters more here than in most peptide research, precisely because the existing evidence base is so concentrated in one research lineage. A pre-registered protocol, published before data collection starts, is the single easiest way to build outside credibility for a new Epitalon study.
Material transparency belongs on this list too. Any lab running new experiments should demand a full certificate of analysis, including purity percentage and impurity profile, for every batch used, since substance characterization was one of the specific concerns FDA reviewers raised about compounded Epitalon products.
Data Peptides’ View on Where the Evidence Actually Stands
The mechanistic case for Epitalon is real and reproducible enough to take seriously. The clinical case for humans is not there yet, and won’t be until someone runs the placebo-controlled trial nobody has run. We think the honest position sits between the two extremes you’ll find online: dismissing the telomerase and telomere data as meaningless ignores a coherent, published mechanism; treating it as proven anti-aging therapy ignores that the entire human efficacy literature is either epithalamin, not Epitalon, or lacks modern trial design altogether.
Reproducibility problems in this field trace back to sourcing as much as study design. When a peptide’s purity or identity is uncertain, every downstream assay result inherits that uncertainty. That’s why we treat batch-level certificates of analysis as a baseline requirement, not a marketing feature, for any lab attempting to build on this evidence base. If you’re running your own replication work and want to compare notes on protocol design or unexpected results, we’d genuinely like to hear from you. The endpoint that matters most right now isn’t a faster path to a headline finding. It’s a safety data set solid enough that the next researcher doesn’t have to guess.
— Data Peptides
Sourcing Research-Grade Epitalon for Laboratory Work
If your protocol calls for Epitalon, the material itself needs to hold up to the same scrutiny as the assay you’re running it through. Data Peptides supplies research-grade Epitalon with third-party batch testing behind every lot, so purity and identity aren’t a variable you’re forced to assume. Certificates of analysis are generally used to provide impurity and potency data, addressing concerns about characterization in compounded supply chains. Every peptide in the shop ships fast and discreetly from a US facility, with support available around the clock for sourcing questions. This is strictly a research chemical intended for laboratory use, not an approved drug for human or animal treatment. If your next step is designing a replication study or a new assay comparison, start by locking down material you can actually trust the numbers from.
Key Papers and Regulatory Documents for Deeper Reading
The 2025 dose-response study on telomerase upregulation and ALT activation is the most detailed modern in vitro data set available and the best starting point for assay design. The PMC review of Epitalon’s properties contextualizes the animal and historical human literature and flags the replication concentration problem directly. The Alzheimer’s Discovery Foundation evidence summary separates epithalamin’s historical clinical record from synthetic Epitalon’s actual data gap. FDA’s July 2026 advisory committee materials lay out the current regulatory posture in full.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Epitalon increases telomere length in human cell lines through telomerase upregulation or ALT activity
- Overview of Epitalon—Highly Bioactive Pineal Tetrapeptide with Promising Properties
- Epithalamin/Epithalon — Evidence summary (Alzheimer’s Discovery Foundation)
FAQ
Does Epitalon Really Work?
It depends what “work” means. In cultured normal human cells, Epitalon reliably increases telomerase activity and telomere length, a reproducible cellular effect. No placebo-controlled human trial has shown it produces a clinical anti-aging or lifespan benefit in people.
How Long Does It Take for Epitalon to Work?
There’s no established human timeline, because no controlled human efficacy trial exists to measure one.
How Much Does Epitalon Cost?
Pricing for research-grade Epitalon varies by supplier and batch documentation quality; current pricing at Data Peptides is available directly on the product page.
What Are the Side Effects of Epitalon?
Historical epithalamin trials reported generally mild adverse events, but that data comes from studies with limited monitoring by modern standards. The larger unknowns are long-term risks, including theoretical cancer concerns tied to the telomerase mechanism, that only a controlled phase 1 safety trial could properly characterize.
Is Epitalon FDA-Approved?
No. Epitalon is not FDA-approved as a drug. A Pharmacy Compounding Advisory Committee vote in July 2026 recommended it for potential 503A compounding listing, but that recommendation is nonbinding and no formal listing has been issued.