

Myostatin inhibitor peptides reliably increase muscle mass and grip strength in rodent models by blocking myostatin’s grip on the ACVRIIB receptor, but no version has cleared human trials for hypertrophy. The most advanced experimental leads, MIF1, MIF2, MIPE-1686, MID-35, and peptide 3d, remain preclinical tools. Regulators have approved none of them, and anti-doping bodies prohibit several outright, which makes the current state of the field one of promising biology paired with a long, unresolved translational gap.
TL;DR:
- No myostatin inhibitor peptides have advanced to human trials, and none are approved or legally permitted for muscle hypertrophy purposes.
- Improved stability through retro-inverso design and chemical modifications significantly increases in vivo durability and muscle growth potential in rodent models.
- Large-animal safety, pharmacokinetics, and off-target effects, especially on cardiac and smooth muscle, remain critical hurdles before human application can be considered.
- Reliable research depends on sourcing peptides with verified purity, lot-specific Certificates of Analysis, and strict laboratory handling protocols to avoid artifacts.
- Even the most potent candidates like peptide 3d and MID-35 are years away from clinical use, emphasizing the need for comprehensive safety and efficacy studies in larger mammals.
Table of Contents
- What Myostatin Inhibitor Peptides Are and How They Work
- Key Peptide Leads and the Design Strategies Behind Them
- The Preclinical Evidence: What Cell and Animal Studies Show
- Why Translation to Humans Remains So Difficult
- How to Evaluate and Source Peptides for Legitimate Research
- Author Credentials and How Data Peptides Supports Reproducible Research
- What the Field Actually Needs Next
- Where to Source Research-Grade Peptides for This Work
- Sources
- FAQ
What Myostatin Inhibitor Peptides Are and How They Work
Myostatin, also known as GDF-8, is the body’s brake pedal on muscle growth. It’s a member of the TGF-beta superfamily, and its entire job is to stop skeletal muscle from getting too big. Knock it out in an animal, genetically or pharmacologically, and you get dramatic, visible hypertrophy. That single observation is the reason an entire subfield of peptide chemistry exists: if myostatin suppresses growth, blocking it should unleash growth.
The mechanism runs through a specific receptor pathway. Myostatin binds to activin receptor type IIB (ACVRIIB) on muscle cell membranes, which triggers a signaling cascade through SMAD2 and SMAD3 proteins. Activated SMAD2/3 moves into the nucleus and suppresses the genetic programs responsible for muscle fiber growth and satellite cell activation. Myostatin inhibitor peptides work by physically getting in the way of this handshake. Some peptides dock directly onto myostatin itself, sterically blocking it from reaching ACVRIIB. Others mimic natural regulatory proteins, particularly the myostatin prodomain and follistatin, molecules the body already produces to keep myostatin in check. Structural work on these prodomain and follistatin interactions shows that effective inhibitors need high binding affinity balanced against controlled reversibility, because permanent, irreversible blockade risks pushing tissue growth past a healthy range.
Follistatin-derived designs deserve their own mention here, since they represent one of the two major structural families in this space alongside synthetic minimal-sequence peptides. Data Peptides’ own overview of follistatin-derived myostatin inhibition covers how these fragments borrow nature’s own inhibitory motif rather than building one from scratch.
Researchers rarely take a peptide’s claimed activity at face value. Confirming that a candidate actually inhibits myostatin signaling, rather than just binding to it weakly or producing an artifact, requires a stack of orthogonal assays:
- Direct binding assays (surface plasmon resonance or ELISA-based) to measure peptide-myostatin affinity and calculate IC50 values
- SMAD2/3 phosphorylation assays in muscle cell lines to confirm the peptide actually blocks downstream signaling, not just binding
- Myoblast proliferation and differentiation assays, typically in C2C12 mouse myoblast cultures, tracking markers like MyoD and myogenin
- Muscle fiber cross-sectional area (CSA) measurements in treated animals, usually via histology after several weeks of dosing
- Functional outcome measures, most commonly grip strength testing and treadmill or rotarod performance in rodents
No single assay tells the whole story. A peptide can show a beautiful IC50 in a binding assay and still fail to move the needle on fiber CSA if it can’t survive long enough in circulation to reach muscle tissue, which is exactly the problem the next section gets into.
Key Peptide Leads and the Design Strategies Behind Them
A handful of experimental sequences dominate the published literature on this topic, and each one illustrates a different design philosophy.
MIF1 and MIF2 are short, 10-residue peptides that emerged as some of the earliest rationally designed myostatin inhibitors. In vitro, both increased myoblast proliferation and boosted myogenic gene expression, and in mouse cardiotoxin injury models, pretreatment improved muscle regeneration compared to untreated controls. The acylated and amidated versions, written as Ac-MIF1 and Ac-MIF2-NH2, showed enhanced activity over the parent sequences, a result documented in the original MIF1 and MIF2 myostatin peptide inhibitor study. N-terminal acylation tends to increase cell permeability and plasma protein binding, which can look like a potency boost in an assay while actually reflecting nonspecific plasma sequestration rather than tighter target engagement, a distinction worth flagging before anyone reads too much into a single fold-change number.
MIPE-1686 is a longer, 16-residue peptide that showed real myostatin inhibitory activity but ran into the classic problem longer peptides face: bigger sequences generally mean more protease cleavage sites, and more cleavage sites mean a shorter functional half-life in vivo. That limitation is exactly what motivated the next design iteration.
MID-35 answers MIPE-1686’s stability problem directly. It’s a retro-inverso D-peptide, meaning the backbone direction is reversed and built from D-amino acids instead of the natural L-form. This trick preserves the side-chain topology that the receptor recognizes while flipping the peptide bond configuration that most proteases are built to cleave. The result, according to the MID-35 development study, is a peptide that retained inhibitory activity comparable to MIPE-1686 in vitro while showing markedly greater resistance to biodegradation and enhanced in vivo potency.
Statistic Callout: MID-35’s retro-inverso D-peptide design produced greater increases in tibialis anterior muscle mass in mice compared to its L-peptide predecessor, driven by improved metabolic stability rather than a change in binding affinity.
Peptide 3d comes out of a hydrophobic residue-directed structural optimization program and stands as one of the most potent minimal myostatin inhibitors reported to date.
Statistic Callout: Peptide 3d posted an in vitro IC50 of 0.32 μM, roughly 11 times more potent than the original minimal inhibitor sequence it was derived from.
That jump came from systematically swapping hydrophobic residues, particularly tryptophan and isoleucine substitutions, and trimming the chain length to concentrate binding contacts rather than dilute them across a longer, floppier sequence.
Follistatin-derived myostatin inhibitory peptides round out the field. These borrow sequence motifs from follistatin’s natural myostatin-binding domain rather than starting from a synthetic scaffold. Structure-activity relationship work in this family, including SAR studies published in Bioorganic & Medicinal Chemistry Letters, found that residue substitution and chain-shortening reliably improved inhibitory activity over the parent follistatin fragment, echoing the same design logic seen in peptide 3d.
Across all five leads, four modification levers keep reappearing:
- Hydrophobic residue optimization to deepen binding-pocket engagement
- N-terminal acylation and C-terminal amidation to extend plasma exposure and improve membrane interaction
- D-amino acid substitution and retro-inverso design to dodge protease recognition entirely
- Chain-shortening and cyclization to concentrate binding energy and reduce conformational flexibility
None of these tricks are unique to myostatin biology. They’re the standard toolkit for turning a fragile linear peptide into something that survives long enough to matter, borrowed from decades of peptide drug design across other targets.
The Preclinical Evidence: What Cell and Animal Studies Show
The evidence base for myostatin inhibitor peptides is almost entirely preclinical, and it splits cleanly into two tiers: cell culture data and rodent in vivo data. Both are encouraging. Neither has been replicated in a large mammal or a human.
In vitro, the pattern across MIF1, MIF2, and their acylated derivatives is consistent. Treated myoblast cultures show increased proliferation rates, upregulated myogenic differentiation markers, and, notably, downregulation of adipogenic markers, suggesting the peptides don’t just push cells toward more muscle, they may also push them away from a fat-storage fate. This dual effect is part of why myostatin inhibition draws interest beyond pure hypertrophy research; it touches on body composition more broadly.
The in vivo rodent data tells a similarly positive but narrower story. In cardiotoxin injury models, animals pretreated with MIF1 or MIF2 showed improved muscle regeneration compared to untreated controls, based on the original MIF peptide inhibitor findings. Separately, MID-35 dosing produced measurable increases in tibialis anterior muscle mass in treated mice, with functional testing in some studies also picking up improved grip strength. Dosing frames across these studies typically involve repeated subcutaneous or intraperitoneal administration over several weeks, with muscle mass and functional endpoints assessed at study end via histology and behavioral testing, rather than single-dose acute experiments.
Worth flagging separately: a randomized, double-blind human trial of a Vicia faba bean hydrolysate product called NPN_1, marketed as PeptiStrong, reported reduced myostatin expression and improved strength recovery after exercise in a small cohort. That trial is real and it is human data, but it’s testing a complex nutritional peptide mixture derived from a food source, not a single-sequence, rationally designed myostatin inhibitory peptide like MIF1 or peptide 3d. Lumping it in with the synthetic peptide leads would be a category error; the PeptiStrong trial results are genuinely interesting but answer a different research question.
Several limitations run through nearly every study in this space, and researchers should weigh them before drawing conclusions:
- Small sample sizes are the norm in rodent cohorts, often in the range of a handful of animals per group, which limits statistical power
- Short study durations mean chronic dosing effects, tolerance, and delayed off-target signals are largely unmeasured
- No large-animal data exists for any of the major peptide leads, which is a significant gap given how often rodent-to-primate translation fails in muscle biology
- PK/PD characterization is thin, with most papers reporting efficacy endpoints without full pharmacokinetic profiling across the dosing interval
That last point matters more than it might seem. A peptide that looks potent on a single-dose curve can behave very differently once you’re asking how it clears, accumulates, and interacts with plasma proteins over weeks of repeated administration.
Why Translation to Humans Remains So Difficult
Peptides face a stability problem before they face anything else. Native L-form peptides get chewed up fast by circulating and tissue proteases, often within minutes to a few hours, which is precisely why the D-amino acid and retro-inverso strategies behind MID-35 exist in the first place. Retro-inverso design reverses backbone chirality while preserving the spatial arrangement of side chains that a receptor recognizes, letting the molecule dodge the very enzymes built to recognize natural peptide bonds. Acylation and cyclization address the same problem from different angles, extending circulation time and locking conformation so the peptide can’t unfold into a shape proteases find easier to cut.
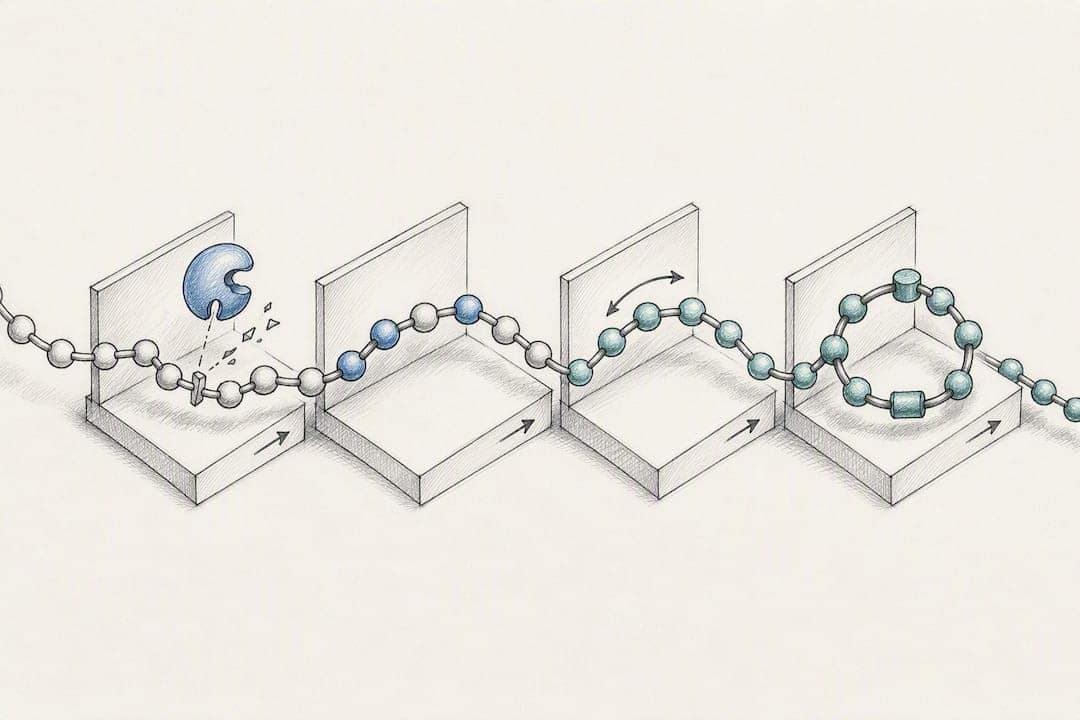
Stability solved is not delivery solved. Even a peptide that survives circulation still needs to reach muscle tissue at a meaningful concentration, and biodistribution studies for most of these leads are sparse. There’s also a legitimate off-target concern: ACVRIIB signaling isn’t exclusive to skeletal muscle. Cardiac tissue and smooth muscle express related activin receptor signaling components, and unchecked, chronic myostatin blockade raises the theoretical risk of off-target hypertrophic changes in tissue you very much do not want growing uncontrolled. Immune response to repeated peptide dosing is a second open question, particularly for modified or non-natural sequences the immune system hasn’t evolved to recognize as self.
The regulatory and ethical picture is unambiguous, even if the science is exciting. As of 2026, there are no FDA-approved myostatin inhibitor peptides for human muscle hypertrophy, and safety and efficacy in humans remain unestablished for the entire class. Many performance-oriented peptides in this general category are also explicitly prohibited under World Anti-Doping Agency rules, which matters both for competitive athletes and for anyone considering off-label use outside a regulated research or clinical trial setting. That combination, no approval and active prohibition, should be the loudest signal in this entire article: the biology is real, but human use sits well outside any established safety framework.
A few priorities should guide safety-focused preclinical work going forward:
- Build cardiac and smooth muscle histology into every chronic dosing study from the start, not as an afterthought after efficacy looks promising.
- Add functional cardiopulmonary monitoring alongside histology, since structural change and functional impairment don’t always show up on the same timeline.
- Characterize immunogenicity for any acylated, D-amino acid, or retro-inverso construct before advancing to longer dosing windows.
- Establish full PK/PD profiles across a repeated-dose interval, not just single-dose curves, before drawing efficacy conclusions.
Pro Tip: Run cardiac and smooth muscle histology in parallel with your primary efficacy endpoints from the very first chronic dosing cohort, not as a follow-up study. Off-target hypertrophic signals are far cheaper to catch at week four of a mouse study than after you’ve already committed to a larger, more expensive translational program.
How to Evaluate and Source Peptides for Legitimate Research
Study design quality starts before the first dose is ever administered, at the sourcing stage. A peptide with unverified purity or an unlisted contaminant profile can produce data that looks like a biological effect but is actually an assay artifact, and that risk is entirely avoidable.
For assay design, pair mechanistic and functional readouts rather than relying on one or the other:
- Mechanistic tier: binding assays for direct affinity, SMAD2/3 phosphorylation assays to confirm pathway engagement, and myogenic transcription factor expression (MyoD, myogenin) to verify downstream activation
- Functional tier: muscle fiber cross-sectional area via histology, grip strength testing, and standardized muscle regeneration models like cardiotoxin injury
On the sourcing side, a short checklist separates a usable peptide lot from a liability:
- Confirm the product carries an explicit research-use-only designation, not a supplement or clinical framing
- Request the Certificate of Analysis for the specific lot, not a generic product-page COA
- Verify third-party purity testing results, ideally via HPLC or mass spectrometry, showing purity at or above 99%
- Check stated endotoxin limits, particularly for anything intended for in vivo administration
- Confirm storage and shipping conditions (typically lyophilized, cold-chain shipped) match what the peptide’s stability profile requires
Statistic Callout: Third-party purity verification at or above 99% is the baseline researchers should expect before running any binding or in vivo assay; anything lower introduces enough variability to compromise IC50 or dose-response data.
Formulation and dosing details deserve piloting before a full study launches, not assuming from the literature. Vehicle choice (saline, PBS, or a carrier suited to the peptide’s solubility profile), administration route (subcutaneous versus intraperitoneal), and PK/PD sampling timepoints all shift results in ways that are easy to underestimate. Impure peptide lots commonly produce two recognizable artifacts: inconsistent dose-response curves that don’t follow a clean sigmoidal shape, and unexplained cytotoxicity in cell culture that has nothing to do with myostatin biology and everything to do with a contaminant. Data Peptides maintains peptide laboratory standards and handling guidance covering exactly these documentation and storage expectations for researchers setting up a new protocol.
Author Credentials and How Data Peptides Supports Reproducible Research
Reproducibility in peptide research depends on knowing exactly what was in the vial, and that’s the gap Data Peptides is built to close. Every product ships as research-use-only, with documentation designed to let a lab verify what they received before it goes anywhere near an assay.
The core proof points researchers rely on:
- Certificates of Analysis available for lot-specific purity and identity verification, not just generic product claims
- Third-party purity testing, with results supporting the 99%+ purity standard referenced throughout the sourcing checklist above
- Research-use-only labeling on every product, keeping the framing consistent with legitimate laboratory application rather than clinical or supplement use
- Technical guides and protocol resources published through the Data Peptides blog, covering handling, storage, and study design considerations
These resources exist specifically to support reproducibility. A COA tied to the exact lot a researcher receives lets that researcher document purity in a methods section rather than taking a manufacturer’s general claim on faith, which matters when a reviewer or collaborator asks how a dose-response inconsistency was ruled out as a purity artifact rather than a biological effect.
None of this changes the fundamental framing that runs through this entire article: these are laboratory research materials, not medical products, and nothing here should be read as dosing guidance for human or animal treatment outside an approved research protocol.
What the Field Actually Needs Next
The gap between a promising mouse study and an approved human therapy is wider than most preclinical papers let on. Closing it doesn’t require a new peptide lead so much as it requires the boring, expensive work that rodent studies skip: pharmacokinetics and pharmacodynamics in a larger mammal, chronic dosing safety data measured in months rather than weeks, and systematic off-target screening across cardiac and smooth muscle tissue rather than a single histology snapshot at study end.
Getting there realistically means bringing in people outside the peptide chemistry lab. Toxicologists need to weigh in before, not after, a chronic dosing study is designed. Regulatory specialists can flag which endpoints a future IND filing would actually require, saving years of rework. Medicinal chemists focused purely on optimization, distinct from the biologists running the efficacy assays, tend to catch stability and formulation problems the discovery team misses because they’re looking for exactly that.
Timeline expectations should stay grounded. Even a peptide lead with a strong story like MID-35 or peptide 3d sits years away from a first human trial, assuming the large-animal safety data even supports moving forward at all. The realistic milestone right now isn’t a human trial. It’s a well-powered, chronic-dosing large-animal safety study that either clears the off-target hypertrophy question or ends the conversation for that specific sequence. Either outcome would be progress.
— Data Peptides
Where to Source Research-Grade Peptides for This Work
Running any of the assays described above depends entirely on starting with a peptide lot you can actually trust, and that’s the specific problem Data Peptides is set up to solve. Every product ships research-use-only with a lot-specific Certificate of Analysis and third-party purity verification at 99% or above, so a purity artifact doesn’t get mistaken for a biological result three weeks into a study.
For researchers setting up a new protocol, the complete ordering guide walks through documentation and compliance details before checkout, and the muscle-focused peptide research guide covers experimental peptide categories relevant to the myogenic pathway work discussed throughout this article. The full catalog is available through the Data Peptides shop, with fast, discreet US shipping and 24/7 support for questions about handling or storage.
Every product on the site is intended strictly for laboratory research, not for human or animal treatment. Researchers should follow their institution’s ethics and regulatory requirements before initiating any study, and nothing in this article substitutes for that oversight.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Development of Potent Myostatin Inhibitory Peptides through Hydrophobic Residue-Directed Structural Modification | ACS Medicinal Chemistry Letters
- Peptides for Bodybuilding: Efficacy, Safety, Types, and More
FAQ
What is the best myostatin inhibitor peptide?
No single peptide qualifies as best; the field currently favors peptide 3d and MID-35 as leading candidates because peptide 3d posted an IC50 of 0.32 μM in vitro and MID-35’s retro-inverso design gave it superior in vivo stability over earlier leads like MIPE-1686.
Is YK11 a myostatin inhibitor?
YK11 is a selective androgen receptor modulator, not a myostatin inhibitor peptide; it’s a synthetic steroid-derived small molecule and belongs to an entirely different drug class from the peptide leads covered in this article.
Is it safe to take myostatin blockers?
Safety in humans is unestablished for the entire myostatin inhibitor peptide class, since no version has been medically approved for hypertrophy, and off-target risks to cardiac and smooth muscle tissue remain a primary unresolved concern in ongoing preclinical work.
What is the most potent myostatin inhibitor?
Among published minimal-sequence peptides, peptide 3d currently holds the strongest reported potency figure, with an in vitro IC50 roughly 11 times stronger than the original minimal inhibitor sequence it was optimized from.